

BLOG
Physician-written perspectives on the latest research and the questions patients ask most. Start with the newest article below, or explore a topic.

Four Things Before Any Peptide
Before any peptide, know four things: peptides are messengers not a fix, baseline labs and history matter (including IGF-1), use a licensed pharmacy with a real prescription, and sleep nutrition and hormones come first. Part 2: oral estrogen can blunt IGF-1 response.
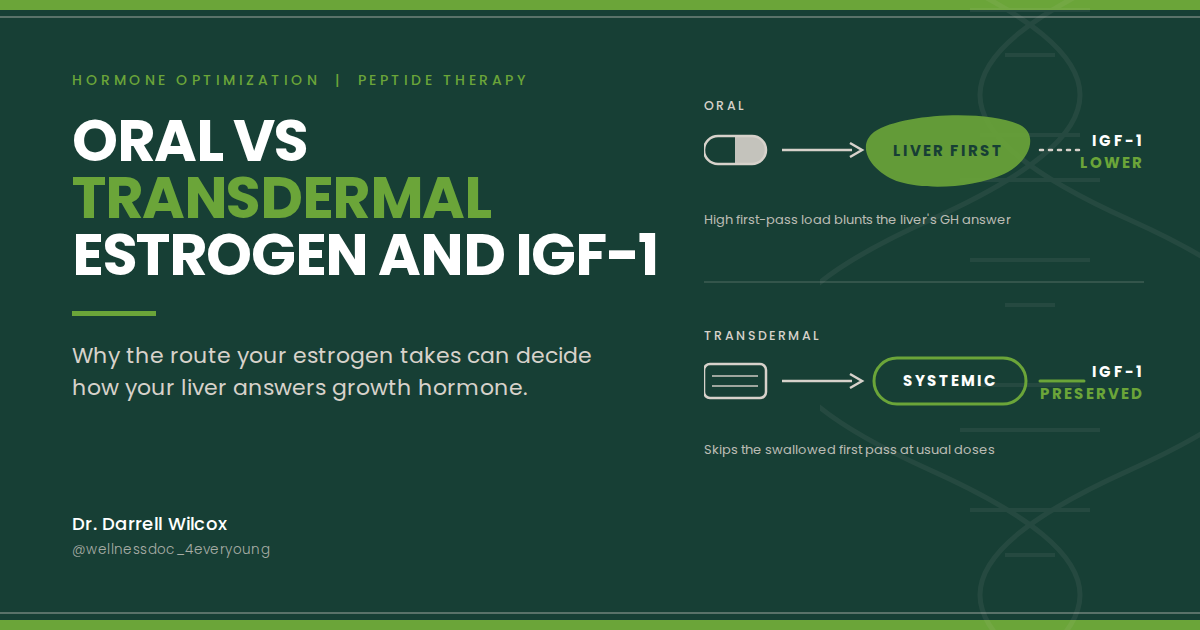
Oral vs Transdermal Estrogen and IGF-1: Why Route Determines Peptide Response
Oral estrogen and transdermal estradiol are not the same for IGF-1. First-pass through the liver helps explain why IGF-1 can stall on oral estrogen even when GH or a GH-axis peptide looks active upstream. Route is part of the foundation.

Your Peptide Isn't Failing. Your Hormones Are.
Peptides amplify signals your body already has to be capable of producing. If your thyroid or sex hormones are underperforming, the peptide has less to work with, and the peptide usually gets blamed first.

Peptides Aren't Magic. They're Messengers.
Peptides are everywhere right now, but most of what's marketed as a shortcut is really a signaling molecule with rules of its own. Here's what actually determines whether a peptide protocol works.

Why You Stop Sleeping Deeply After 40 — And What the Growth Hormone Pulse Has to Do With It
Your deep sleep and your growth hormone don't decline separately — they decline together. Here's the mechanism most physicians never explain, and what the data shows about restoring it.

Sermorelin vs. Ipamorelin/CJC-1295 vs. Tesamorelin: Which Growth Hormone Peptide Is Right for You?
A physician's guide to the real differences between sermorelin, ipamorelin/CJC-1295, and tesamorelin — three distinct GHRH peptides with different mechanisms, potency, and ideal use cases. Written by Darrell Wilcox, MD.